Uncommon Descent Serving The Intelligent Design Community

The Frontline Doctors put some “plausible” mechanisms for Hydroxychloroquine on the table

Categories
Academic Freedom
Cell biology
Medicine
rhetoric
Share
Facebook
Twitter/X
LinkedIn
Flipboard
Print
Email

In their July 28 seminar, the Frontline Doctors Group led by Dr Simone Gold, have put some plausible mechanisms for HCQ based cocktails on the table. These were noted on in an augmentation to an earlier post, but deserve headlining in their own right:

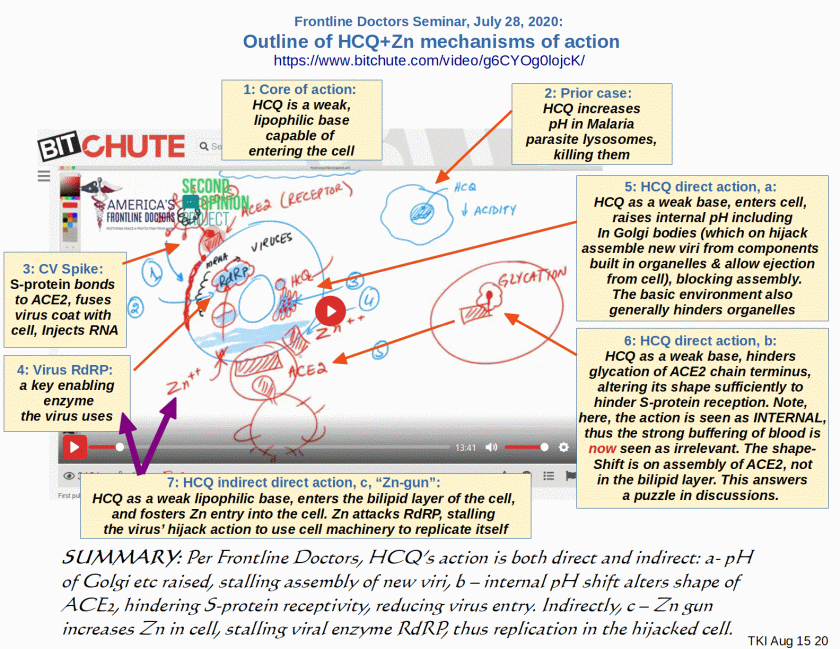
Dr Frieden OP: >>I have found at Bit Chute, a July 28 Frontline Doctors seminar which describes several mechanisms of action. Accordingly, I take liberty to annotate a screenshot, summarising several mechanisms of action described by these Doctors [cf. here for their references], but which are hard to find because of now almost pervasive censorship:
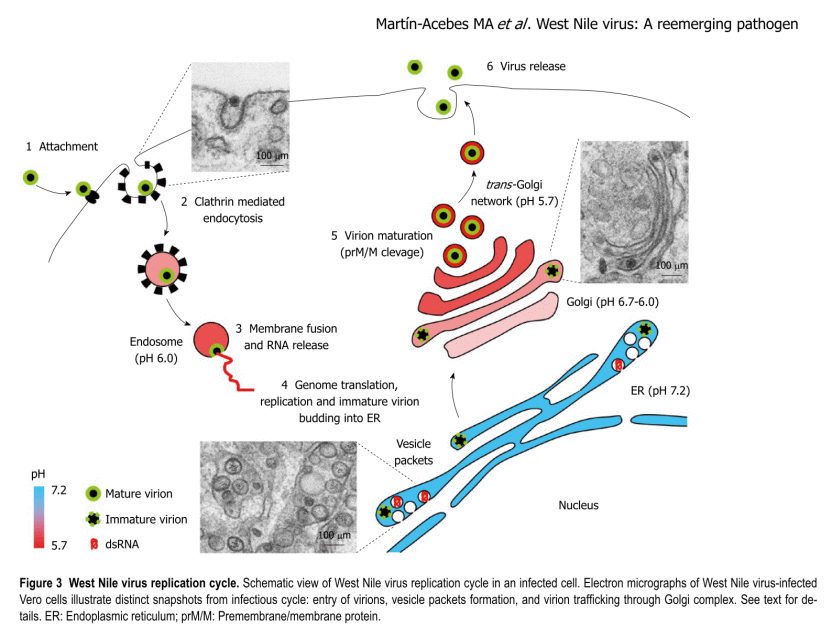
I add, that the above suggests a fairly similar viral attack process to the West Nile Virus (which is also an RNA virus), e.g.:
U/D, Mon Aug 16: I further add, a “DrBeen” — Dr Mobeen Syed — educational video, just found — this is the presenter summarised above:

https://www.youtube.com/watch?v=yjkPdwlhI8A

I note, this first answers a puzzle on the mode of action, shape-shift of ACE2: the shift is INTERNAL to the cell by hindering “glycation” of the final AA (thus prior to exposure to buffering of blood etc), altering the shape enough to hamper S-protein reception. This reduces fusion with bilipid layer and RNA injection.

Other direct mechanisms as noted, reduce intracellular acidity thus action of organelles. They highlight stalling of assembly of new viri in the Golgi bodies, with implication of blocking export of fresh viri, thus hampering the multiplication chain. The by now well known indirect activity is that as a lipophilic molecule, HCQ enters the cell bilipid layer membrane, acting as a Zn ionophore, i.e. it “shoots” Zn into the cell. Zn in turn hinders a key viral enzyme, RdRP.

Thus, we see a plausible picture of causal action, involving multiple, synergistic effects. This lends credibility to the use of HCQ-based cosctails in treating the early viral phases of CV19.>>

Unfortunately, WP for UD is not set up to embed BitChute videos.

An odd bit of support for this, is that HCQ/CQ have been used as fish tank cleaner for about 40 years. The complex animals (the fish) live, but the crud from several kingdoms, dies. That points to attack modes that hit core cell processes, such as we may summarise:
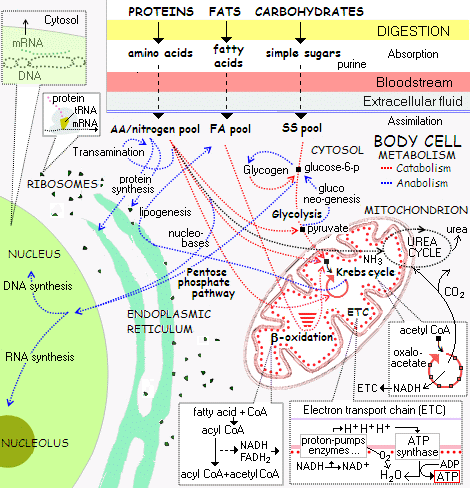
That seems to be what is now on the table, through the effects of pH shifting, as proposed. In short, we have reasonable mechanisms to go with the reports of doctors who are treating CV 19 in the early, viral phase, with vulnerable group patients:
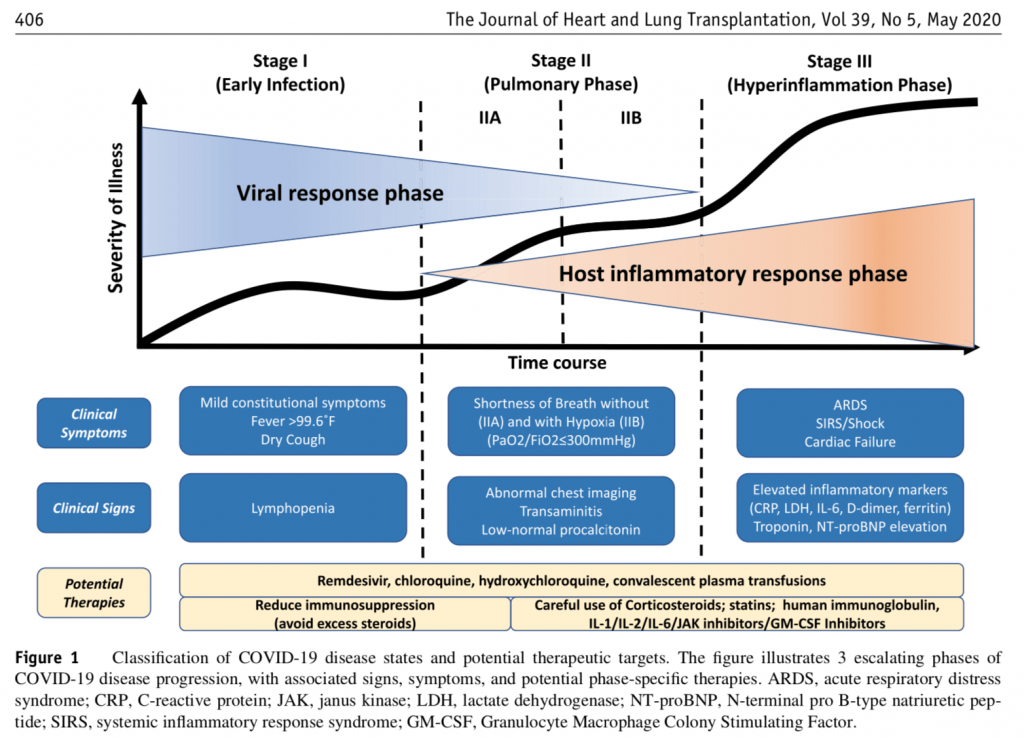
From this, we can freely say that it is going to be a challenge to refute the framework of issues and implicit model being presented in the open letter to Dr Fauci:

>>There is currently no recommended pharmacologic early outpatient treatment for individuals in the flu stage of the illness, correct?

It is true that COVID-19 is much more lethal than the flu for high-risk individuals such as older patients and those with significant comorbidities, correct?

Individuals with signs of early COVID-19 infection typically have a runny nose, fever, cough, shortness of breath, loss of smell, etc., and physicians send them home to rest, eat chicken soup etc., but offer no specific, targeted medications, correct?

These high-risk individuals are at high risk of death, on the order of 15% or higher, correct?

So just so we are clear—the current standard of care now is to send clinically stable symptomatic patients home, “with a wait and see” approach?

Are you aware that physicians are successfully using Hydroxychloroquine combined with Zinc and Azithromycin as a “cocktail” for early outpatient treatment of symptomatic, high-risk, individuals?

Have you heard of the “Zelenko Protocol,” for treating high-risk patients with COVID 19 as an outpatient?

Have you read Dr. Risch’s article in the American Journal of Epidemiology of the early outpatient treatment of COVID-19?

Are you aware that physicians using the medication combination or “cocktail” recommend use within the first 5 to 7 days of the onset of symptoms, before the illness impacts the lungs, or cytokine storm evolves?

Again, to be clear, your recommendation is no pharmacologic treatment as an outpatient for the flu—like symptoms in patients that are stable, regardless of their risk factors, correct?

Would you advocate for early pharmacologic outpatient treatment of symptomatic COVID-19 patients if you were confident that it was beneficial?

Are you aware that there are hundreds of physicians in the United States and thousands across the globe who have had dramatic success treating high-risk individuals as outpatients with this “cocktail?”

Are you aware that there are at least 10 studies demonstrating the efficacy of early outpatient treatment with the Hydroxychloroquine cocktail for high-risk patients — so this is beyond anecdotal, correct?

If one of your loved ones had diabetes or asthma, or any potentially complicating comorbidity, and tested positive for COVID-19, would you recommend “wait and see how they do” and go to the hospital if symptoms progress?

Even with multiple studies documenting remarkable outpatient efficacy and safety of the Hydroxychloroquine “cocktail,” you believe the risks of the medication combination outweigh the benefits?

Is it true that with regard to Hydroxychloroquine and treatment of COVID-19 infection, you have said repeatedly that “The Overwhelming Evidence of Properly Conducted Randomized Clinical Trials Indicate No Therapeutic Efficacy of Hydroxychloroquine (HCQ)?”

But NONE of the randomized controlled trials to which you refer were done in the first 5 to 7 days after the onset of symptoms- correct?

All of the randomized controlled trials to which you refer were done on hospitalized patients, correct?

Hospitalized patients are typically sicker that outpatients, correct?

None of the randomized controlled trials to which you refer used the full cocktail consisting of Hydroxychloroquine, Zinc, and Azithromycin, correct?

While the University of Minnesota study is referred to as disproving the cocktail, the meds were not given within the first 5 to 7 days of illness, the test group was not high risk (death rates were 3%), and no zinc was given, correct?

Again, for clarity, the trials upon which you base your opinion regarding the efficacy of Hydroxychloroquine, assessed neither the full cocktail (to include Zinc + Azithromycin or doxycycline) nor administered treatment within the first 5 to 7 days of symptoms, nor focused on the high-risk group, correct?

Therefore, you have no basis to conclude that the Hydroxychloroquine cocktail when used early in the outpatient setting, within the first 5 to 7 days of symptoms, in high risk patients, is not effective, correct?

It is thus false and misleading to say that the effective and safe use of Hydroxychloroquine, Zinc, and Azithromycin has been “debunked,” correct? How could it be “debunked” if there is not a single study that contradicts its use?

Should it not be an absolute priority for the NIH and CDC to look at ways to treat Americans with symptomatic COVID-19 infections early to prevent disease progression?

The SARS-CoV-2/COVID-19 virus is an RNA virus. It is well-established that Zinc interferes with RNA viral replication, correct?

Moreover, is it not true that hydroxychloroquine facilitates the entry of zinc into the cell, is a “ionophore,” correct?

Isn’t also it true that Azithromycin has established anti-viral properties?

Are you aware of the paper from Baylor by Dr. McCullough et. al. describing established mechanisms by which the components of the “HCQ cocktail” exert anti-viral effects?

So- the use of hydroxychloroquine, azithromycin (or doxycycline) and zinc, the “HCQ cocktail,” is based on science, correct?>>

Let us see how the “game” moves forward beyond this point. END

PS: As an extra, here is Dr Zelenko:

https://www.youtube.com/watch?v=3ywj-PZTt4g

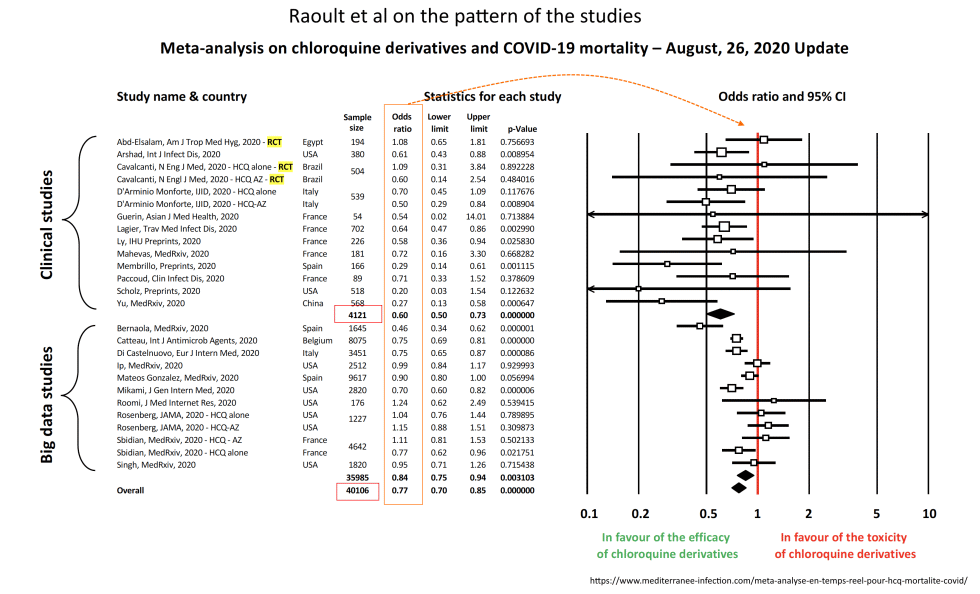
PPS: As a further extra, Aug 29, HT Jerry, Raoult et al on the pattern of cases and studies, involving 40,000+ cases:
Comments
Any bets that reporters have been assigned by Washington Post and NY Times to look at the downside of plasma therapy? The Washington Post did a hit piece yesterday on the decision to build ventilators and how they are all wasted and sitting in warehouses. It appears that similar objections are being made about plasma as were with HCQ. No RCT so how can we know? It also appears to be aimed at those who have reached a serious stage of virus progression. Results so far are positive but not dramatic. But it hasn’t been looked at with scrutiny so we will see. But it will be political I bet.jerry
August 24, 2020
August
08
Aug
24
24
2020
04:04 AM
4
04
04
AM
PST
JaD, it should be blatantly obvious that antibody-rich plasma will have an immunity transfer effect. Isn't that parallel to what happens to infants taking "first milk" from their moms, colustrum isn't it? Then, there is antivenin (which can make you quite ill but saves your life). KFkairosfocus
August 24, 2020
August
08
Aug
24
24
2020
02:49 AM
2
02
49
AM
PST
H'mm: A summary by professor Risch (vid transcript) on the track record of gold standard fallacies, blocking bactrin against secondary infection for 2 years in the AIDS crisis:
Dr. Risch: This has gone on before. Now we have Dr. Fauci denying that any evidence exists of benefit (of HCQ). And that’s pervaded the FDA. The FDA has relied on Dr. Fauci and his NIH advisory groups to make the statements saying that there is no benefit in using hydroxychloroquine in outpatients. And this is counter to the facts of the case. The evidence is overwhelming… Dr. Fauci and the FDA are doing the same thing that was done in 1987 [--> he demanded placebo control studies,. leading to a 2-year delay] and that’s led to the deaths of hundreds of thousands of Americans [--> maybe a bit overstated, or is he including secondary deaths?] that could have been saved by the usage of this drug! And this is the same thing that the FDA has done. It’s outrageous! People need to be writing or calling their congressman or senators and complaining that this is not the way the country should work
The article notes on balance of studies:
** 53 global studies that show positive results with HCQ on COVID-19 ** 14 global studies that show neutral or negative results with HCQ on COVID-19 ** 10 of those 14 negative studies were of patients in very late stages of the disease ** 2 of those 14 negative studies were by the same doctor in Minnesota ** 1 of the studies used by Dr. Fauci from a Brazilian outlet was debunked ** The last study be Lancet was later found fraudulent and retracted
Points to ponder KFkairosfocus
August 24, 2020
August
08
Aug
24
24
2020
02:44 AM
2
02
44
AM
PST
Speaking to reporters from the White House Sunday, Trump said the FDA has "issued an emergency use authorization ... for a treatment known as convalescent plasma." https://www.foxnews.com/politics/trump-announces-emergency-authorization-of-breakthrough-coronavirus-treatment But just wait. The politics is yet to start. As they were leaving the room a reporter (sounded to me like Jim Acosta) yelled out to FDA commissioner Stephen Hahn, “Were you pressured to make this decision?” It never ends!john_a_designer
August 23, 2020
August
08
Aug
23
23
2020
03:19 PM
3
03
19
PM
PST
Strange- living has the same side effects as HCQ- nausea and diarrhea. :) Discussing HCQ with its opponents also has that same side effect- well the nausea part, anyway.ET
August 23, 2020
August
08
Aug
23
23
2020
10:13 AM
10
10
13
AM
PST
HCQ protects heart
hydroxychloroquine is protective to the heart, not Harmful: A systematic review Conclusions HCQ and azithromycin do not cause TDP cardiac mortality. HCQ decreases cardiac events. HCQ should not be restricted in use for COVID 19 patients because of fear of cardiac mortality.
https://www.ncbi.nlm.nih.gov/pmc/articles/PMC7439006/ So should it be given to everyone who has C19 for this reason? Sounds like we should add it to the water so everyone can benefit. That would solve all the debate issues. By the way I am being sarcastic. HCQ does have some side effects - nausea and diarrhea.jerry
August 23, 2020
August
08
Aug
23
23
2020
09:43 AM
9
09
43
AM
PST
Several scientists challenge negative analysis of HCQ studies.
Experts contest studies that saw no benefits in chloroquine A group of 37 Brazilian and international researchers publishes an open letter stating that there was an error in the interpretation of the statistical tests.
https://translate.google.com/translate?hl=&sl=auto&tl=en&u=https%3A%2F%2Fveja.abril.com.br%2Fsaude%2Fespecialistas-contestam-estudos-que-nao-viram-beneficios-na-cloroquina%2F&sandbox=1 On a similar vein
An open letter of concern about statistical analysis
Some of the same people https://drive.google.com/file/d/1NZOJ57fM0RTaHD1t_9w2iua7lUJhOgWT/view From a statistician
Reading a scientific paper: easy Identifying important, key flaws in a scientific paper: often pretty difficult Convincing the authors of the key flaws: nearly impossible Convincing authors and editors to set the record straight bc self correcting science: are you kidding?
jerry
August 23, 2020
August
08
Aug
23
23
2020
08:43 AM
8
08
43
AM
PST
Soul searching for the anti HCQ faction
China approves chloroquine (instead of hydroxychloroquine) against covid-19
https://www.archyde.com/china-approves-chloroquine-instead-of-hydroxychloroquine-against-covid-19/ Will the switch change our negative posters or will they double down? It will be a soul searching time for them. More good news but not for Bill Gates and Fauci
T cells — not antibodies — may be key to long-term COVID-19 immunity. What are they? It’s the million dollar question: Can we develop long-term immunity against SARS-CoV-2, the virus that has taken the lives of over 783,000 people worldwide as of Aug. 19. Although there are no definitive answers, scientists believe there might be a light at the end of the immunity tunnel. Several studies, both peer reviewed and not, have looked beyond antibodies to the rest of the highly complex immune system. Now, all eyes are on T cells and B cells — key players in the response against foreign invaders that emerge after the body has been exposed to a pathogen.
There may be no need for a vaccine. https://www.yahoo.com/news/t-cells-not-antibodies-may-225818680.html
Parts of London and New York have already achieved 'substantial' immunity, Harvard epidemiologists say
https://www.yahoo.com/news/parts-london-york-already-achieved-113750524.html Will they need vaccination?jerry
August 23, 2020
August
08
Aug
23
23
2020
08:17 AM
8
08
17
AM
PST
Jerry,
I’m not sure Rhampton understands what he posts…how much he understands seems limited. He just reposted the Boulware study which I’m sure he doesn’t understand… My guess is if he finds some article somewhere that is negative on HCQ he will post it without knowing the implications.
Are you sure he/she is really human. Maybe Rhampton is a bot.john_a_designer
August 23, 2020
August
08
Aug
23
23
2020
06:32 AM
6
06
32
AM
PST
Earth to RH7- Dr. Zelenko's challenge stands. His protocol includes zinc. I posted 2 papers saying that vitamin D deficiency led to the deaths of many patients. So either you are incapable of reading or you are willfully ignorant.ET
August 23, 2020
August
08
Aug
23
23
2020
04:50 AM
4
04
50
AM
PST
tells us all we need to know.
I’m not sure Rhampton understands what he posts. I’ve asked him more than once if he is a native English speaker. He is obviously familiar with English but how much he understands seems limited. He just reposted the Boulware study which I’m sure he doesn’t understand. My guess is if he finds some article somewhere that is negative on HCQ he will post it without knowing the implications. He thinks our concern is solely about HCQ when our concerns are about saving lives. HCQ is just one of many ways we have focused on. As a result the negative purveyors including RHampton have painted themselves into a corner of advocating death just to win the HCQ argument. Very revealing!!! He is not the only one. There is an obsession with finding anyone who is positive here guilty of a wrong position on something even if it is bad grammar. Even if it forces them into advocating death in large numbers. It’s not just here but in any political argument in a lot of places.jerry
August 23, 2020
August
08
Aug
23
23
2020
04:43 AM
4
04
43
AM
PST
RH7, that you imagine the right population -- the vulnerable [typ 60+, those with certain diseases etc] -- is nonsense tells us all we need to know. KFkairosfocus
August 23, 2020
August
08
Aug
23
23
2020
04:19 AM
4
04
19
AM
PST
Why don’t you ask Dr Raoult why his protocol doesn’t require Zinc or Vitamins C and D?rhampton7
August 22, 2020
August
08
Aug
22
22
2020
03:18 PM
3
03
18
PM
PST
(Brazil) We conducted a multicenter, randomized, open-label, three-group, controlled trial involving hospitalized patients with suspected or confirmed Covid-19 who were receiving either no supplemental oxygen or a maximum of 4 liters per minute of supplemental oxygen. Patients were randomly assigned in a 1:1:1 ratio to receive standard care, standard care plus hydroxychloroquine at a dose of 400 mg twice daily, or standard care plus hydroxychloroquine at a dose of 400 mg twice daily plus azithromycin at a dose of 500 mg once daily for 7 days. The primary outcome was clinical status at 15 days as assessed with the use of a seven-level ordinal scale (with levels ranging from one to seven and higher scores indicating a worse condition) in the modified intention-to-treat population (patients with a confirmed diagnosis of Covid-19). Safety was also assessed. A total of 667 patients underwent randomization; 504 patients had confirmed Covid-19 and were included in the modified intention-to-treat analysis. As compared with standard care, the proportional odds of having a higher score on the seven-point ordinal scale at 15 days was not affected by either hydroxychloroquine alone (odds ratio, 1.21; 95% confidence interval [CI], 0.69 to 2.11; P=1.00) or hydroxychloroquine plus azithromycin (odds ratio, 0.99; 95% CI, 0.57 to 1.73; P=1.00). Prolongation of the corrected QT interval and elevation of liver-enzyme levels were more frequent in patients receiving hydroxychloroquine, alone or with azithromycin, than in those who were not receiving either agent. Among patients hospitalized with mild-to-moderate Covid-19, the use of hydroxychloroquine, alone or with azithromycin, did not improve clinical status at 15 days as compared with standard care. (Funded by the Coalition Covid-19 Brazil and EMS Pharma; ClinicalTrials.gov number, NCT04322123. opens in new tab.) https://www.nejm.org/doi/full/10.1056/NEJMoa2019014rhampton7
August 22, 2020
August
08
Aug
22
22
2020
03:16 PM
3
03
16
PM
PST
Randomized, double-blind, placebo-controlled trial conducted from 22 March through 20 May 2020. (ClinicalTrials.gov: NCT04308668) Internet-based trial across the United States and Canada (40 states and 3 provinces). Symptomatic, nonhospitalized adults with laboratory-confirmed COVID-19 or probable COVID-19 and high-risk exposure within 4 days of symptom onset. Oral hydroxychloroquine (800 mg once, followed by 600 mg in 6 to 8 hours, then 600 mg daily for 4 more days) or masked placebo. Measures: Symptoms and severity at baseline and then at days 3, 5, 10, and 14 using a 10-point visual analogue scale. The primary end point was change in overall symptom severity over 14 days. Of 491 patients randomly assigned to a group, 423 contributed primary end point data. Of these, 341 (81%) had laboratory-confirmed infection with severe acute respiratory syndrome coronavirus 2 (SARS-CoV-2) or epidemiologically linked exposure to a person with laboratory-confirmed infection; 56% (236 of 423) were enrolled within 1 day of symptoms starting. Change in symptom severity over 14 days did not differ between the hydroxychloroquine and placebo groups (difference in symptom severity: relative, 12%; absolute, ?0.27 points [95% CI, ?0.61 to 0.07 points]; P = 0.117). At 14 days, 24% (49 of 201) of participants receiving hydroxychloroquine had ongoing symptoms compared with 30% (59 of 194) receiving placebo (P = 0.21). Medication adverse effects occurred in 43% (92 of 212) of participants receiving hydroxychloroquine versus 22% (46 of 211) receiving placebo (P < 0.001). With placebo, 10 hospitalizations occurred (2 non–COVID-19–related), including 1 hospitalized death. With hydroxychloroquine, 4 hospitalizations occurred plus 1 nonhospitalized death (P = 0.29). Only 58% of participants received SARS-CoV-2 testing because of severe U.S. testing shortages. Hydroxychloroquine did not substantially reduce symptom severity in outpatients with early, mild COVID-19. https://www.acpjournals.org/doi/10.7326/M20-4207rhampton7
August 22, 2020
August
08
Aug
22
22
2020
03:13 PM
3
03
13
PM
PST
What is a "post exposure prophylaxis"? Holy cow, people are confused. Where's the zinc? Where's the vitamin's C and D?ET
August 22, 2020
August
08
Aug
22
22
2020
03:11 PM
3
03
11
PM
PST
We conducted a multicenter, open label, randomized controlled trial in Catalonia (Spain) between March 17, and May 26, 2020. Eligible Covid-19 cases were non-hospitalized adult patients with recently confirmed SARS-CoV-2 infection and less than five days of symptoms. Patients were assigned to receive HCQ (800 mg on day 1, followed by 400 mg once daily for 6 days) or no antiviral treatment (not-placebo controlled). Study outcomes were the reduction of viral RNA load in nasopharyngeal swabs up to 7 days after treatment start, patient disease progression using the WHO scale up to 28 days, and time to complete resolution of symptoms. Adverse events were assessed up to 28 days. A total of 293 patients were eligible for intention-to-treat analysis: 157 in the control arm and 136 in the intervention arm. The mean age was 41.6 years (SD 12.6), mean viral load at baseline was 7.90 (SD 1.82) Log10 copies/mL, and median time from symptom onset to randomization was 3 days. No significant differences were found in the mean reduction of viral load at day 3 (-1.41 vs. -1.41 Log10 copies/mL in the control and intervention arm, respectively; difference 0.01 [95% CI -0.28;0.29]) or at day 7 (-3.37 vs. -3.44; d –0.07 [-0.44;0.29]). This treatment regimen did not reduce risk of hospitalization (7.1%, control vs. 5.9%, intervention; RR 0.75 [0.32;1.77]) nor shortened the time to complete resolution of symptoms (12 days, control vs. 10 days, intervention; p = 0.38). No relevant treatment-related AEs were reported. In patients with mild Covid-19, no benefit was observed with HCQ beyond the usual care. https://academic.oup.com/cid/advance-article/doi/10.1093/cid/ciaa1009/5872589rhampton7
August 22, 2020
August
08
Aug
22
22
2020
03:08 PM
3
03
08
PM
PST
A Randomized Trial of Hydroxychloroquine as Postexposure Prophylaxis for Covid-19 We conducted a randomized, double-blind, placebo-controlled trial across the United States and parts of Canada testing hydroxychloroquine as postexposure prophylaxis. We enrolled adults who had household or occupational exposure to someone with confirmed Covid-19 at a distance of less than 6 ft for more than 10 minutes while wearing neither a face mask nor an eye shield (high-risk exposure) or while wearing a face mask but no eye shield (moderate-risk exposure). Within 4 days after exposure, we randomly assigned participants to receive either placebo or hydroxychloroquine (800 mg once, followed by 600 mg in 6 to 8 hours, then 600 mg daily for 4 additional days). The primary outcome was the incidence of either laboratory-confirmed Covid-19 or illness compatible with Covid-19 within 14 days. We enrolled 821 asymptomatic participants. Overall, 87.6% of the participants (719 of 821) reported a high-risk exposure to a confirmed Covid-19 contact. The incidence of new illness compatible with Covid-19 did not differ significantly between participants receiving hydroxychloroquine (49 of 414 [11.8%]) and those receiving placebo (58 of 407 [14.3%]); the absolute difference was ?2.4 percentage points (95% confidence interval, ?7.0 to 2.2; P=0.35). Side effects were more common with hydroxychloroquine than with placebo (40.1% vs. 16.8%), but no serious adverse reactions were reported. After high-risk or moderate-risk exposure to Covid-19, hydroxychloroquine did not prevent illness compatible with Covid-19 or confirmed infection when used as postexposure prophylaxis within 4 days after exposure. (Funded by David Baszucki and Jan Ellison Baszucki and others; ClinicalTrials.gov number, NCT04308668. opens in new tab.) https://www.nejm.org/doi/full/10.1056/NEJMoa2016638rhampton7
August 22, 2020
August
08
Aug
22
22
2020
03:05 PM
3
03
05
PM
PST
Hydroxychloroquine, a drug commonly used in the treatment of rheumatoid arthritis, has received much negative publicity for adverse events associated with its authorisation for emergency use to treat patients with COVID-19 pneumonia. We studied the safety of hydroxychloroquine, alone and in combination with azithromycin, to determine the risk associated with its use in routine care in patients with rheumatoid arthritis. The study included 956?374 users of hydroxychloroquine, 310?350 users of sulfasalazine, 323?122 users of hydroxychloroquine plus azithromycin, and 351?956 users of hydroxychloroquine plus amoxicillin. Hydroxychloroquine treatment appears to have no increased risk in the short term among patients with rheumatoid arthritis, but in the long term it appears to be associated with excess cardiovascular mortality. The addition of azithromycin increases the risk of heart failure and cardiovascular mortality even in the short term. We call for careful consideration of the benefit–risk trade-off when counselling those on hydroxychloroquine treatment. https://www.thelancet.com/journals/lanrhe/article/PIIS2665-9913(20)30276-9/fulltextrhampton7
August 22, 2020
August
08
Aug
22
22
2020
02:58 PM
2
02
58
PM
PST
B’OH Pre esxposure RCT was done, don’t remember the details, but I did post it. KF, what is this right population nonsense? Who is that? Did Raoult describe this or is this your own addition? Also, at least one RCT was done with people exposed to COVID but pre-symptomatic. I also posted this before.rhampton7
August 22, 2020
August
08
Aug
22
22
2020
02:57 PM
2
02
57
PM
PST
There is definitely a cost to lockdowns but the cost of doing nothing is death.
As you so often advocate. Doing nothing when there are effective treatments. So you advocate for death. Lockdowns kill in other ways. Economically and socially. There is no mandate to classify any other death as due to the lockdown when there may be hundreds of thousands that have already happened, in process or coming in the next year due to the lockdown.
What this pandemic has shown us is the ingenuity of humans. Many of us are learning that you can effectively work from home, and that many businesses don’t need to have all staff in the office at the same time
Yes, but it is the rapid displacing of tens of millions of Americans and maybe billions worldwide. Few who comment here witness first hand the destruction going on as they are safe.
Designer and branded masks have become a market opportunity. As have expanded on-line market place
Doesn’t help the tens of millions out of work which are heavily skewed to woman and poor.jerry
August 22, 2020
August
08
Aug
22
22
2020
12:18 PM
12
12
18
PM
PST
MMT, nope, you fail the Economics, dismal science test. For months I have pointed out that once CV19 broke out of containment, large numbers of deaths were inevitable. Pandemics cost lives and lockdowns cost lives. Deaths of despair, deaths due to foregone or fatally postponed medical interventions and more are attributable deaths. For example just for the US, statistics of recessions seem to suggest for every 10 - 24 mn down in GDP, a life is lost. That does not count lives lost due to people not going to deal with strokes and heart attacks due to the shift in accessibility or to the shift in psychology. For cancer, time lost tracks to lives lost. And yes, electives covers a lot, where apparently there is a suggested 40% down on going for rapid medical attention. Panic comes with a price tag. Policy makes therefore face a dismal choice that many lives will be lost regardless of what they do, and headlined direct lives lost may trade off against potentially more lives lost less directly; leading to a devil's negotiation in excessively polarised political systems. And more can be said. KF PS: As for do nothing, there is no significant local or national government that has done nothing.kairosfocus
August 22, 2020
August
08
Aug
22
22
2020
10:58 AM
10
10
58
AM
PST
Wow, no one says to do nothing. A healthy nation wouldn't have had to lock down. Why we aren't focusing on that proves that we are not a smart race.ET
August 22, 2020
August
08
Aug
22
22
2020
10:49 AM
10
10
49
AM
PST
MMT, evidence is evidence. Cumulative evidence is just that, cumulative. A few weeks back, mechanisms were a consideration and thanks to Dr Been and the Frontline Doctors, we now have readily accessible, more detailed answers than hitherto. In the case of HCQ, there is no doubt it can transit gut--> body and act in cells. Here, we have direct action mechanisms and Zn gun promotion mechanisms. These fit into the framework that CV19 has a viral phase [perhaps 5 - 7 days typical], providing a window of opportunity for intervention. Further, the narrative of being unsafe has been strongly corrected. Next, we have thousands of cases of effective use, with direct demonstration of sharp falls in viral load in 1 - 2 days and clearing in 5 - 7, similar to many other effective drugs; backed by patient and doctor reports of getting rapid relief in that sort of window (my son just went into an episode subsequent to sharing a corn on the cob with a 3 year old cousin). Such have long since been charted and reported. Such is in the further context of ethically responsible and epistemically valid observational studies on thousands of cases that show something like reducing deaths in vulnerable groups by up to 90%. But no, in steps the gold standard fallacy and all of that is swept away. Where, since placebo controls are not in fact universally demanded historically or currently [say, mask use and lockdowns] it is increasingly clear that HCQ does not fit a preferred narrative and agenda, with damaging direct and indirect consequences. A sorry situation. KFkairosfocus
August 22, 2020
August
08
Aug
22
22
2020
10:44 AM
10
10
44
AM
PST
There is definitely a cost to lockdowns but the cost of doing nothing is death. What this pandemic has shown us is the ingenuity of humans. Many of us are learning that you can effectively work from home, and that many businesses don’t need to have all staff in the office at the same time. I wouldn’t want to be in the commercial real estate market now and into the future. Many businesses are going to be downsizing their office footprint. Designer and branded masks have become a market opportunity. As have expanded on-line market place.Mac McTavish
August 22, 2020
August
08
Aug
22
22
2020
08:32 AM
8
08
32
AM
PST
Cost of lockdowns.
Merkel Warns Europe Against Reviving New Virus Lockdowns German Chancellor Angela Merkel called on European leaders to work together to avoid renewed lockdowns as a resurgence of the coronavirus threatens already battered economies.
https://www.msn.com/en-us/news/world/merkel-warns-europe-against-reviving-new-virus-lockdowns/ar-BB18chNj?li=BBnbcA1 A wide ranging political analysis but the first item focuses on the cost of lockdowns.
Ten 2020 Issues, Policies, Personalities — and Chance #1 1)The Lockdown. More or less, Americans followed the March–June lockdowns that seemed at least for a while to slow the viral spread. Of course, “flattening the curve” to prevent hospital overcrowding soon insidiously morphed into the impossible task of stopping the virus by shutting down the economy and quarantining the population. I suppose the theory was “we had to destroy the health of a society to ensure it was healthy.” We know from Sweden and the gradual diminution in cases in the hardest hit states of the U.S. Northeast that the virus has a say in such policies. It seems determined to have an initial spike followed by a lull and yet another lesser spike, before it finds it harder to infect more vulnerable victims, as antibodies and T-cells increasingly ensure either growing de facto immunity or asymptotic infection, all while herd immunity rises and the virus plays itself. We will soon, perhaps in a year or so, learn of the real tally of forced quarantines — the substance abuse, child abuse, retrogression in millions of young students denied K–12 learning and supervision, missed health diagnostics and preventative care, and delayed or cancelled surgeries. And the tab will likely be far higher than the coronavirus death count and the post-viral fatigue and morbidity of stricken but recovering patients. In other words, there were never blue/red choices or Democratic/Republican ones, but only bad and worse and all in between.
https://outline.com/Ur2Sg6jerry
August 22, 2020
August
08
Aug
22
22
2020
07:48 AM
7
07
48
AM
PST
Good question! Who is suppressing the use of HCQ?
On May 29, [FDA Commissioner Dr. Stephen] Hahn stated: “Prescribing a product for uses not specifically included in the official labeling is common in the practice of medicine. In oncology and mental health, many patients are treated this way.” He notes that with COVID-19 “health care professionals are looking for every possible treatment option for their patients,” and that patients and their doctors “must ultimately decide what treatment is likely to be best for the individual patient.” Dr. Hahn recognizes that “hydroxychloroquine and chloroquine have received particular attention. Both are FDA-approved to treat or prevent malaria, and hydroxychloroquine is also approved to treat autoimmune conditions such as chronic discoid lupus erythematosus, systemic lupus erythematosus in adults, and rheumatoid arthritis. They have been prescribed for years to help patients with these debilitating, or even deadly, diseases and have a well-established safety profile for these conditions.”
https://apnews.com/a3e99384b955d60f4c0fd7c738c6b2a8 If this is true, why is its use being restricted by pharmacy boards in certain U.S. states like Texas? So again, who’s suppressing HCQ’s off-label use? If it’s not the FDA, it’s either (1) big pharma, (2) the mainstream media (3) left wing politicians or (4) some combination of all three.john_a_designer
August 22, 2020
August
08
Aug
22
22
2020
06:45 AM
6
06
45
AM
PST
Understanding despair. How to counteract it.
The Battle for Pandemic Sanity: Hydroxychloroquine Efficacy vs. Its Suppression
It’s difficult to understand where the despair comes from. But there is plenty of sensible ways to counteract it. Read this for a partial explanation for the suppression of HCQ. It’s not everything but explains a lot. A very good analysis. If already linked, I apologize. Something I did not know. Some government medical agencies Including the CDC get money from the drug companies. So “Follow the Money.” https://www.globalresearch.ca/hydroxychloroquine-efficacy-suppression/5718676 The ongoing question is why does Fauci lie so much?jerry
August 22, 2020
August
08
Aug
22
22
2020
06:06 AM
6
06
06
AM
PST
More hope!
Artemisia Annua Could Be Promising Treatment for COVID-19 Recent lab studies by chemists at the Max Planck Institute of Colloids and Interfaces (Potsdam, Germany) in close collaboration with virologists at Freie Universität Berlin have shown that extract from the medicinal plant Artemisia annua, also known as Sweet Wormwood, is active against SARS-CoV-2, the virus that has caused the COVID-19 pandemic. The new potential treatment has been added to the University of Kentucky’s innovative clinical trial for experimental COVID-19 therapies, which was launched by leaders from UK’s Markey Cancer Center, College of Medicine and College of Pharmacy in May.
https://uknow.uky.edu/research/artemisia-annua-could-be-promising-treatment-covid-19jerry
August 22, 2020
August
08
Aug
22
22
2020
04:58 AM
4
04
58
AM
PST
the clinical trials completed to date don’t support its efficacy in treating COVID. I wish it were different, but hopes can’t be forced into reality.
This is a nonsense statement. No one in the world has presented a relevant study which shows it’s not effective. And there are over 50 analysis that show efficacy. It is this cavalier attitude that has led to tens of thousands dying unnecessarily. It is a safe, extremely inexpensive drug that has been used widely with positive results. How could anyone morally argue against it. There is no way to justify such a stance. Why is such nonsense repeated again and again? Why isn’t their valid criticism of each analysis? It may say more about the critics than the protocol. https://c19study.com/jerry
August 22, 2020
August
08
Aug
22
22
2020
04:36 AM
4
04
36
AM
PST
1 … 8 9 10 11 12 13