Uncommon Descent Serving The Intelligent Design Community

The Frontline Doctors put some “plausible” mechanisms for Hydroxychloroquine on the table

Categories
Academic Freedom
Cell biology
Medicine
rhetoric
Share
Facebook
Twitter/X
LinkedIn
Flipboard
Print
Email

In their July 28 seminar, the Frontline Doctors Group led by Dr Simone Gold, have put some plausible mechanisms for HCQ based cocktails on the table. These were noted on in an augmentation to an earlier post, but deserve headlining in their own right:

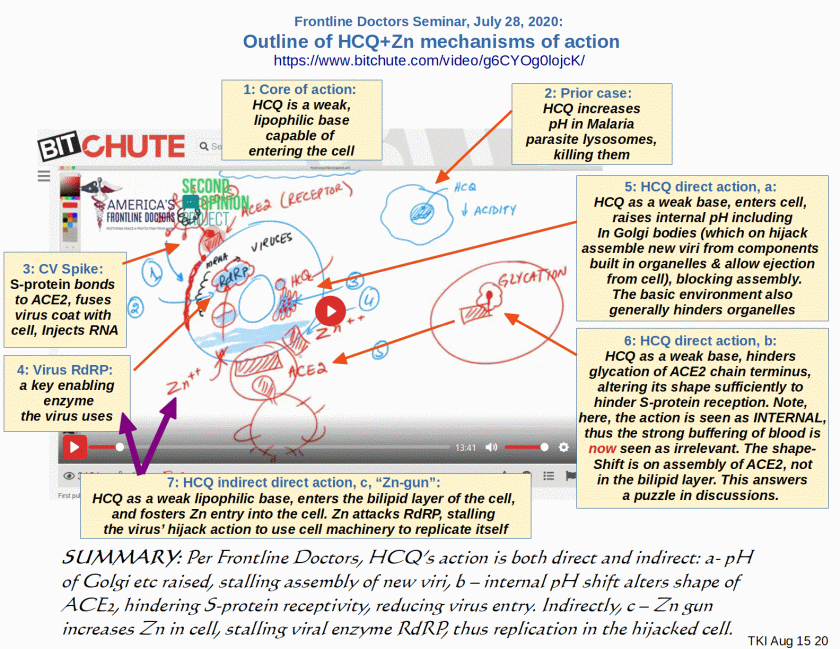
Dr Frieden OP: >>I have found at Bit Chute, a July 28 Frontline Doctors seminar which describes several mechanisms of action. Accordingly, I take liberty to annotate a screenshot, summarising several mechanisms of action described by these Doctors [cf. here for their references], but which are hard to find because of now almost pervasive censorship:
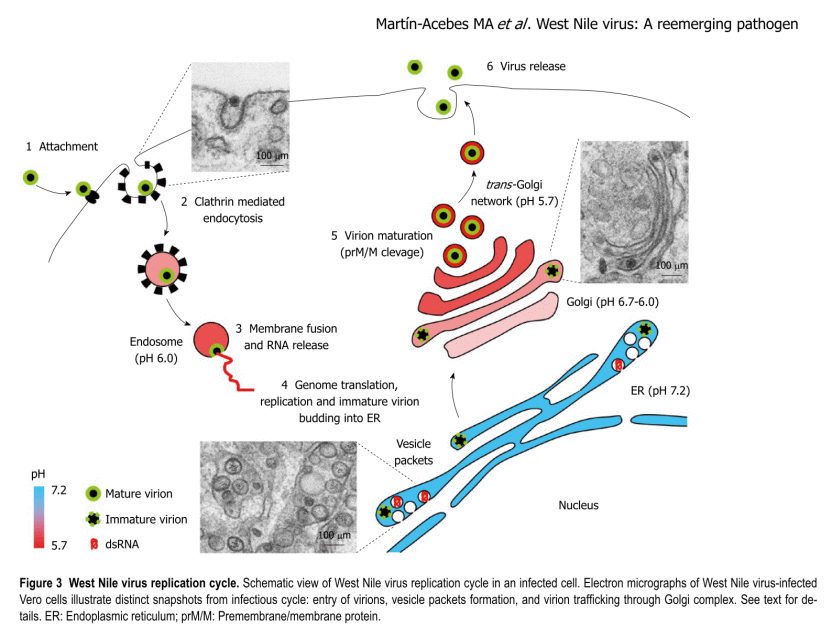
I add, that the above suggests a fairly similar viral attack process to the West Nile Virus (which is also an RNA virus), e.g.:
U/D, Mon Aug 16: I further add, a “DrBeen” — Dr Mobeen Syed — educational video, just found — this is the presenter summarised above:

https://www.youtube.com/watch?v=yjkPdwlhI8A

I note, this first answers a puzzle on the mode of action, shape-shift of ACE2: the shift is INTERNAL to the cell by hindering “glycation” of the final AA (thus prior to exposure to buffering of blood etc), altering the shape enough to hamper S-protein reception. This reduces fusion with bilipid layer and RNA injection.

Other direct mechanisms as noted, reduce intracellular acidity thus action of organelles. They highlight stalling of assembly of new viri in the Golgi bodies, with implication of blocking export of fresh viri, thus hampering the multiplication chain. The by now well known indirect activity is that as a lipophilic molecule, HCQ enters the cell bilipid layer membrane, acting as a Zn ionophore, i.e. it “shoots” Zn into the cell. Zn in turn hinders a key viral enzyme, RdRP.

Thus, we see a plausible picture of causal action, involving multiple, synergistic effects. This lends credibility to the use of HCQ-based cosctails in treating the early viral phases of CV19.>>

Unfortunately, WP for UD is not set up to embed BitChute videos.

An odd bit of support for this, is that HCQ/CQ have been used as fish tank cleaner for about 40 years. The complex animals (the fish) live, but the crud from several kingdoms, dies. That points to attack modes that hit core cell processes, such as we may summarise:
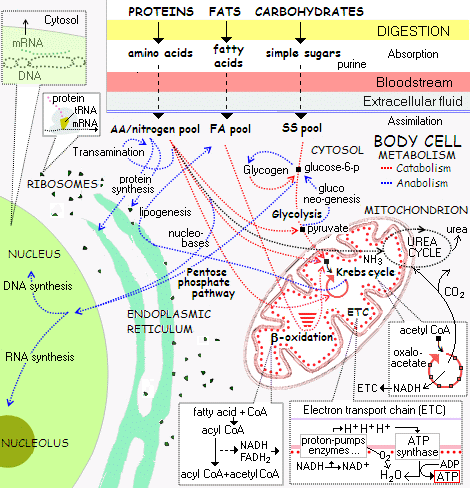
That seems to be what is now on the table, through the effects of pH shifting, as proposed. In short, we have reasonable mechanisms to go with the reports of doctors who are treating CV 19 in the early, viral phase, with vulnerable group patients:
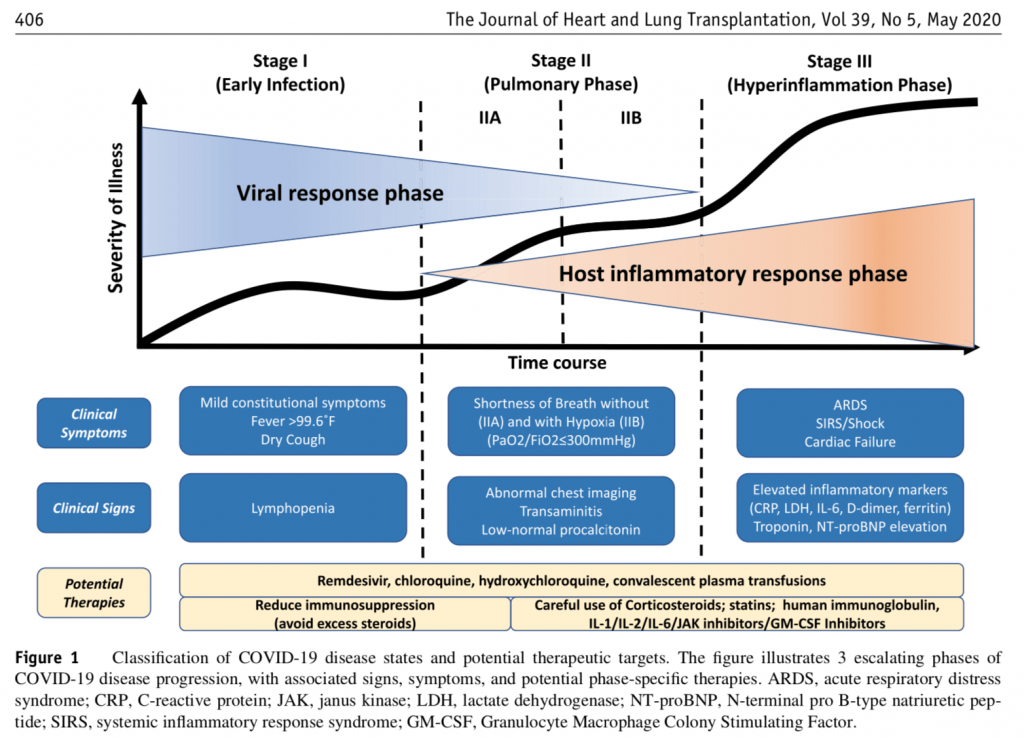
From this, we can freely say that it is going to be a challenge to refute the framework of issues and implicit model being presented in the open letter to Dr Fauci:

>>There is currently no recommended pharmacologic early outpatient treatment for individuals in the flu stage of the illness, correct?

It is true that COVID-19 is much more lethal than the flu for high-risk individuals such as older patients and those with significant comorbidities, correct?

Individuals with signs of early COVID-19 infection typically have a runny nose, fever, cough, shortness of breath, loss of smell, etc., and physicians send them home to rest, eat chicken soup etc., but offer no specific, targeted medications, correct?

These high-risk individuals are at high risk of death, on the order of 15% or higher, correct?

So just so we are clear—the current standard of care now is to send clinically stable symptomatic patients home, “with a wait and see” approach?

Are you aware that physicians are successfully using Hydroxychloroquine combined with Zinc and Azithromycin as a “cocktail” for early outpatient treatment of symptomatic, high-risk, individuals?

Have you heard of the “Zelenko Protocol,” for treating high-risk patients with COVID 19 as an outpatient?

Have you read Dr. Risch’s article in the American Journal of Epidemiology of the early outpatient treatment of COVID-19?

Are you aware that physicians using the medication combination or “cocktail” recommend use within the first 5 to 7 days of the onset of symptoms, before the illness impacts the lungs, or cytokine storm evolves?

Again, to be clear, your recommendation is no pharmacologic treatment as an outpatient for the flu—like symptoms in patients that are stable, regardless of their risk factors, correct?

Would you advocate for early pharmacologic outpatient treatment of symptomatic COVID-19 patients if you were confident that it was beneficial?

Are you aware that there are hundreds of physicians in the United States and thousands across the globe who have had dramatic success treating high-risk individuals as outpatients with this “cocktail?”

Are you aware that there are at least 10 studies demonstrating the efficacy of early outpatient treatment with the Hydroxychloroquine cocktail for high-risk patients — so this is beyond anecdotal, correct?

If one of your loved ones had diabetes or asthma, or any potentially complicating comorbidity, and tested positive for COVID-19, would you recommend “wait and see how they do” and go to the hospital if symptoms progress?

Even with multiple studies documenting remarkable outpatient efficacy and safety of the Hydroxychloroquine “cocktail,” you believe the risks of the medication combination outweigh the benefits?

Is it true that with regard to Hydroxychloroquine and treatment of COVID-19 infection, you have said repeatedly that “The Overwhelming Evidence of Properly Conducted Randomized Clinical Trials Indicate No Therapeutic Efficacy of Hydroxychloroquine (HCQ)?”

But NONE of the randomized controlled trials to which you refer were done in the first 5 to 7 days after the onset of symptoms- correct?

All of the randomized controlled trials to which you refer were done on hospitalized patients, correct?

Hospitalized patients are typically sicker that outpatients, correct?

None of the randomized controlled trials to which you refer used the full cocktail consisting of Hydroxychloroquine, Zinc, and Azithromycin, correct?

While the University of Minnesota study is referred to as disproving the cocktail, the meds were not given within the first 5 to 7 days of illness, the test group was not high risk (death rates were 3%), and no zinc was given, correct?

Again, for clarity, the trials upon which you base your opinion regarding the efficacy of Hydroxychloroquine, assessed neither the full cocktail (to include Zinc + Azithromycin or doxycycline) nor administered treatment within the first 5 to 7 days of symptoms, nor focused on the high-risk group, correct?

Therefore, you have no basis to conclude that the Hydroxychloroquine cocktail when used early in the outpatient setting, within the first 5 to 7 days of symptoms, in high risk patients, is not effective, correct?

It is thus false and misleading to say that the effective and safe use of Hydroxychloroquine, Zinc, and Azithromycin has been “debunked,” correct? How could it be “debunked” if there is not a single study that contradicts its use?

Should it not be an absolute priority for the NIH and CDC to look at ways to treat Americans with symptomatic COVID-19 infections early to prevent disease progression?

The SARS-CoV-2/COVID-19 virus is an RNA virus. It is well-established that Zinc interferes with RNA viral replication, correct?

Moreover, is it not true that hydroxychloroquine facilitates the entry of zinc into the cell, is a “ionophore,” correct?

Isn’t also it true that Azithromycin has established anti-viral properties?

Are you aware of the paper from Baylor by Dr. McCullough et. al. describing established mechanisms by which the components of the “HCQ cocktail” exert anti-viral effects?

So- the use of hydroxychloroquine, azithromycin (or doxycycline) and zinc, the “HCQ cocktail,” is based on science, correct?>>

Let us see how the “game” moves forward beyond this point. END

PS: As an extra, here is Dr Zelenko:

https://www.youtube.com/watch?v=3ywj-PZTt4g

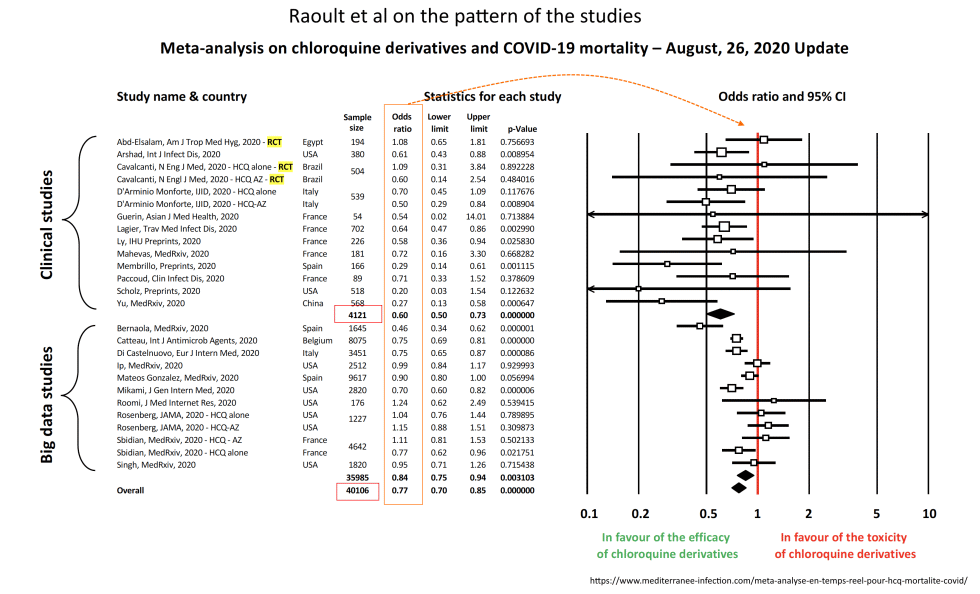
PPS: As a further extra, Aug 29, HT Jerry, Raoult et al on the pattern of cases and studies, involving 40,000+ cases:
Comments
FDA and HCQ
Senators Demand Answers on Hydroxychloroquine from the FDA, Reports the Association of American Physicians & Surgeons (AAPS) The senators ask the FDA to provide the Committee, by Aug 25, with all information pertaining to FDA decisions that discourage the outpatient use of HCQ for early treatment or prophylaxis of COVID-19, and also “any public statements or records that FDA has issued to clarify that the FDA does not regulate the practice of medicine and that state governments may not regulate the sale or prohibit the sale of prescription drugs.”
https://apnews.com/a3e99384b955d60f4c0fd7c738c6b2a8jerry
August 22, 2020
August
08
Aug
22
22
2020
04:31 AM
4
04
31
AM
PST
And yet there are doctors and patients swearing to its efficacy. There is even a $200,000 challenge for anyone who can demonstrate the protocol is ineffective. THAT is the reality. There is even a scientifically sound prophylaxis. More than half of the deaths could have been prevented just by proper nutrition.ET
August 21, 2020
August
08
Aug
21
21
2020
06:27 PM
6
06
27
PM
PST
KF
Notice, the mechanisms are still on the table.
I don’t think anybody has been questioning the possible mechanisms. What’s in question is whether these translate into measurable benefits in vivo. Unfortunately for all of us, the clinical trials completed to date don’t support its efficacy in treating COVID. I wish it were different, but hopes can’t be forced into reality.Mac McTavish
August 21, 2020
August
08
Aug
21
21
2020
05:53 PM
5
05
53
PM
PST
Notice, the mechanisms are still on the table.kairosfocus
August 21, 2020
August
08
Aug
21
21
2020
04:35 PM
4
04
35
PM
PST
Here is a recent article, by psychiatrist Norman Doidge, which gives a good history of the currently evolving controversy around HCQ and covid-19. It takes an especially close look at the way it is being researched and some of the ethical questions, such as relying RCT’s, in exclusion to any other empirical approach, in the midst of a pandemic.
We tend to think of methodology as a dry question that has nothing to do with morality. The methodologist asks what is the best technique to get at the most certainty most quickly, and usually answers: a randomized control trial, or RCT. But in medicine, moral concerns can’t be humanely divorced from methodology. Early in a pandemic, when we know little, there is a moral imperative to start gathering data. While RCTs are often (but not always, see below) the best kind of study, they take more time, and involve randomly assigning, say, half the patients to a new unknown but promising treatment, and half to either a placebo (sugar pill) or treatment-as-usual (which might be nothing). They are a type of experiment… That is one reason why so many researchers, like Raoult, opted for observational studies, in which as many patients as possible are treated. This is not a matter of choosing a design that is “fatally flawed,” it is a matter of choosing a design that is not unnecessarily fatal to the patients. It’s is not sloppiness (as some of his critics would allege), but being true to the study question as he saw it: How can we save as many lives as possible. These observational studies could begin almost immediately, and didn’t require the slow approval process that RCTs require, in part because of the moral dilemmas they raise.
https://www.tabletmag.com/sections/science/articles/hydroxychloroquine-morality-tale Indeed we need to keep in mind that science begins with observation, gathering data.john_a_designer
August 21, 2020
August
08
Aug
21
21
2020
02:23 PM
2
02
23
PM
PST
It's called natural selection. And given that A) democratic governors basically killed tens of thousands of their elderly, and B) how this virus attacks the unhealthy, I am surprised the death total is so low. I predicted 500,000 dead, on the low end, for the first year, in the USA.ET
August 21, 2020
August
08
Aug
21
21
2020
01:51 PM
1
01
51
PM
PST
Mac McTavish is very "saddened" about the 40+ million abortions performed since 1973 (only in the USA). He cries.Truthfreedom
August 21, 2020
August
08
Aug
21
21
2020
01:44 PM
1
01
44
PM
PST
We are on track to hit another couple sad milestones in the next little while. 180,000 deaths before the end of the weekend, and over 200,000 by the first day of fall. I don’t think anyone here would have predicted 200,000 COVID deaths in a seven month period.Mac McTavish
August 21, 2020
August
08
Aug
21
21
2020
01:37 PM
1
01
37
PM
PST
Update on Ivermectin from Australia
Australian GPs Can Legally Prescribe Ivermectin Triple Therapy Protocol — Professor Thomas Borody The Centre for Digestive Diseases issued today a press release titled “Ivermectin Triple Therapy Protocol for COVID-19 Released to Australian GPs for Infected Elderly and Frontline Workers.” As we previously covered, this early treatment protocol combines ivermectin with doxycycline and zinc. “Triple therapy specialist Professor Thomas Borody, famous for curing peptic ulcers using a triple antibiotic therapy saving millions of lives, today released the COVID-19 treatment protocol to Australian GPs, who can legally prescribe it to their COVID-19 positive patients. They can also prescribe it as a preventative medication. Borody says this could be the fastest and safest way to end the pandemic in Australia within 6-8 weeks.”
https://bit.ly/3j10ItD See how fast the use of this treatment spreads if at all even in Australia.jerry
August 21, 2020
August
08
Aug
21
21
2020
09:50 AM
9
09
50
AM
PST
what does that letter have to do with Covid-19?
Specifically nothing but coming after a massive censoring of information about C19 it just reemphasizing where we are on free speech. Everything is political including free speech. One can always censor anything by saying it does not meet some sort of guideline. Throwing in the word, "community" makes is seem caring when it is anything but. They are after censoring legitimate points of view which includes at the same time the censoring of information about C19.jerry
August 21, 2020
August
08
Aug
21
21
2020
08:32 AM
8
08
32
AM
PST
Jerry @ 70 what does that letter have to do with Covid-19?Bob O'H
August 21, 2020
August
08
Aug
21
21
2020
07:46 AM
7
07
46
AM
PST
Mac- you are an ignorant infant. Deal with that before you go blaming others for your issues.ET
August 21, 2020
August
08
Aug
21
21
2020
07:33 AM
7
07
33
AM
PST
Let me repeat a point that I raised earlier @ 53.
Before the U.S. was shut down due to Covid-19 did the CDC do a randomized double-blind study of the effectiveness (and risks) of a nationwide shutdown? Where is the study written up? I’d like to read it. From what I remember the CDC was more or less shooting from the hip. But I suppose I could be wrong about that. Again, where are the studies?
Then recently on another thread one of our regular interlocutors said this:
The promotion of HCL before its efficacy has been demonstrated is also ethically suspect.
I pointed out that… By the same logic:
The mandate of a nationwide lockdown before its efficacy has been demonstrated is also ethically suspect. The mandate of social distancing and mask wearing before its efficacy has been demonstrated is also ethically suspect. Well actually the only thing that is ethically suspect is the logic. But it doesn’t take much to convince the lemmings.
https://uncommondescent.com/intelligent-design/cs-lewis-covid-19-and-scientism/#comment-710237 Now let’s look at what the recommends about wearing masks.
CDC recommends that people wear masks in public settings and when around people who don’t live in your household, especially when other social distancing measures are difficult to maintain. Masks may help prevent people who have COVID-19 from spreading the virus to others. (emphasis added)
https://www.cdc.gov/coronavirus/2019-ncov/prevent-getting-sick/cloth-face-cover-guidance.html So what’s the ethical difference of using a drug that’s been around for over 60 years, is already in wide use and has been proven not only safe but very safe and the use of masks simply because they “may help prevent people who have COVID-19 from spreading the virus to others”? Once again, the claim that the commenters here, who are arguing for the widespread use of HCQ, have been making is there is good evidence (the testimony of physicians treating Covid-19 patients) for efficacy of the drug in the early phases of the disease. So what’s the alternative? We should just continue to let people die? How is that ethical?john_a_designer
August 21, 2020
August
08
Aug
21
21
2020
07:31 AM
7
07
31
AM
PST
ET, you really are incapable of behaving like an adult. I’m surprised that any website allows you to comment.Mac McTavish
August 21, 2020
August
08
Aug
21
21
2020
07:13 AM
7
07
13
AM
PST
Is C19 unique? Of course every virus is unique but in what ways is C19 different from other viruses? One major difference is the age effect. This has been explained by the susceptibility of older people due to inadequate immune systems and prevalence of comorbidities. But hasn’t that always been true? So why this one? Why now? I haven’t seen any answers that make sense. If anyone has insight it would be useful. One characteristic that had temporary interest was that younger people have less ACE2 receptors. Is ACE2 the key? Do other viruses attack the ACE2 receptors? Attacking ACE2 explains the cardiovascular problems due to clotting? Here is a comparison with the 1957 flu epidemic. World - 1957 dpm (deaths per million) 383 dpm- 2020 84 dpm (estimate for year) so much higher in 1957 US - 1957 674 dpm - 2020 680 dpm (estimate for year) UK - 1957 641 dpm - 2020 673 dpm (estimate for year) So about same in US and UK and very much higher than rest of world.jerry
August 21, 2020
August
08
Aug
21
21
2020
05:47 AM
5
05
47
AM
PST
And "extremely limited data" means that data does exist. That means you lied, again. It's pathetically sad that Mac tells me to grow up all the while Mac acts like an ignorant infantET
August 21, 2020
August
08
Aug
21
21
2020
05:37 AM
5
05
37
AM
PST
Mac, obviously you have reading comprehension issues. The SCIENCE supports the use of those OTC supplements. Read the reference papers or continue to wallow in your ignorance. I don't care but just don't think your ignorance is an argument.
Not exactly the definitive claim that you have repeatedly made.
Again, my claim is based on the SCIENCE, that is why you are so confused.ET
August 21, 2020
August
08
Aug
21
21
2020
05:35 AM
5
05
35
AM
PST
Is the virus more of a political not a medical problem
Attorneys General In 20 States Tell Social Media Giants To Censor More Free Speech, Keith Ellison Among Signers
https://www.nationalistreview.net/2020/08/19/attorneys-general-in-20-states-tell-social-media-giants-to-censor-more-free-speech-keith-ellison-among-signers/ All Democrats. They are admitting they believe they can control votes by suppression of speech. The result is they are killIng people who will die from C19
Misinformation. They use that word throughout the letter, because that’s what this is really about. It’s not about so-called hate speech (which is really just distasteful, yet legally protected, free speech). This is about censoring wrong-think. It’s about censoring stories they don’t want you to read.
Of course some of this misinformation is true and actually information but just not convenient to a particular political ideology. For example, we could probably have a long discussion here on which comments contained misinformation. Then there is what exactly is misinformation? People are moving to Parler and Rumble to prevent suppression of their points of view.jerry
August 21, 2020
August
08
Aug
21
21
2020
05:11 AM
5
05
11
AM
PST
Hopefully true
Delhi’s Sero Survey Results Show We Are Fast Approaching Herd Immunity': Epidemiologist J P Muliyil
https://www.outlookindia.com/website/story/india-news-delhis-sero-survey-results-show-we-are-fast-approaching-herd-immunity-epidemiologist-j-p-muliyil/357205
Q) One-fourth of Delhi developed immunity without a vaccine. Is that a good sign? The result is pretty encouraging. This is herd immunity. A vaccine is supposed to do this. Unfortunately, we don’t have one. It would have been tragic if there were only deaths and no immunity. This result means we are not completely lost. The news of the vaccine from Oxford is also good. Once we reach herd immunity, we can unlock gradually. The reason is that lockdown doesn’t prevent transmission, it only causes inconveniences and affects the industries. Despite all the containment efforts, people got a high level of immunity. That means the virus is happily moving around.
jerry
August 21, 2020
August
08
Aug
21
21
2020
05:00 AM
5
05
00
AM
PST
BO'H: Apparently it STILL hasn't registered that there are grave ethical issues involved, or that full bore investigations to test through the ponderous protocols will by and large deliver too late for there to be a timely pandemic response, much less that there is already reasonable, responsible evidence in hand. I don't need to further point out the built to fail biases of studies that have been promoted: too late in the U/L trajectory, wrong focus (not on the vulnerable), trying to separate components of a synergistic treatment, etc. Remember, just on Zn, something like a 1/4 of the population is Zn deficient, which is a real confounding issue if there is refusal to use an integrated protocol. Something drastic will have to be done about how such medical studies are conducted, but that is for later, again, as that will take too much time. Indeed, it seems they are going to do some sort of emergency acceleration on vaccines, which face the hurdle that after decades of trying, there are no established vaccines for corona virus epidemics, they mutate too fast duet o their nature. Already, it is too late for the main surge of this pandemic and it is clear that tens to hundreds of thousands have needlessly died because of the gold standard fallacy and linked selective hyperskepticism. KFkairosfocus
August 21, 2020
August
08
Aug
21
21
2020
04:07 AM
4
04
07
AM
PST
kf @ 63 -
RH7, it has long since been shown that the “gold standard” tests you pointed to are misdirected, being post viral growth phase or the wrong segments of pop, those not showing the vulnerability.
The lack of such studies is surely a criticism to be levelled at people like Raoult, who had the resources to run them, but chose not to. FWIW, I'm not sure what you mean by the "post viral growth phase", but RCTs are being done both the pre-exposure prophylaxis and post-exposure prophylaxis stages. The post-exposure prophylaxis trials both show no effect (I thought a pre-exposure trial had too, but I can't find a reference to that).Bob O'H
August 21, 2020
August
08
Aug
21
21
2020
12:03 AM
12
12
03
AM
PST
ET
That isn’t what the EVMS states. Clearly you have reading comprehension issues.
Well, I was paraphrasing. But here is what they say.
While there is extremely limited data, the following “cocktail” may have a role in the prevention/mitigation of COVID-19 disease. It should however be noted that a recent publication suggests that melatonin my reduce the risk of COVID-19 infection.[1] This cocktail is cheap, safe, and widely available. • Vitamin C 500 mg BID (twice daily) and Quercetin 250-500 mg BID [2-8] • Zinc 50-75 mg/day (elemental zinc). Zinc lozenges are preferred. After 1 month, reduce the dose to 30-50 mg/day. [2,9-13] • Melatonin (slow release): Begin with 0.3mg and increase as tolerated to 2 mg at night [1,14-17] • Vitamin D3 2000-4000 u/day [18-25] • Optional: Famotidine 20-40 mg/day [26]
Not exactly the definitive claim that you have repeatedly made.
The only reason “extremely limited data” for the efficacy of OTC cocktail exists is because no one is running any trials- or they haven’t reported them.
The only reason there is limited evidence for the efficacy of crystal therapy and pyramid power is because no one is running any trials- or they haven’t reported them.Mac McTavish
August 20, 2020
August
08
Aug
20
20
2020
09:36 PM
9
09
36
PM
PST
From the EVMS:
11. For prophylaxis and treatment of the early symptomatic phase we suggest the combination of Quercetin (a plant polyphenol), Vitamin C and Zinc. This is based on intriguing basic science data which indicates that: a. Zinc is essential for innate and adaptive immunity.[10] In addition, Zinc inhibits RNA dependent RNA polymerase in vitro against SARS-CoV-2 virus.[9] b. Quercetin has direct viricidal properties against a range of viruses, including SARS-CoV2.[3,7] In addition, quercetin acts as a zinc ionophore. [148] c. Vitamin C improves the potency of Quercetin and has antiviral activity.[3] 12. It should also be noted that Vitamin D may be a very powerful prophylactic and treatment strategy against COVID-19. [18-25] Vitamin D deficiency explains, in part, the enormous geographic variation in mortality of this disease.
The only reason "extremely limited data" for the efficacy of OTC cocktail exists is because no one is running any trials- or they haven't reported them. What we would need is the nutrient information for everyone who had the virus, those who are asymptomatic and those who cannot get infected.ET
August 20, 2020
August
08
Aug
20
20
2020
08:57 PM
8
08
57
PM
PST
Mac:
Are these the same OTC supplements that the EVSM state have not been demonstrated to have any prophylactic benefits but that there is no harm in taking them?
That isn't what the EVMS states. Clearly you have reading comprehension issues. Acartia Eddie George had the same reading comprehension issue. Weird.ET
August 20, 2020
August
08
Aug
20
20
2020
08:47 PM
8
08
47
PM
PST
RH7, it has long since been shown that the "gold standard" tests you pointed to are misdirected, being post viral growth phase or the wrong segments of pop, those not showing the vulnerability. And yet, once there was a crack in a study, and the effectiveness manifested itself. Your insistence on such cites in the face of cogent correction shows us just how dangerous a fallacy is involved in erecting such "gold standards" that lock out valid empirical evidence. KF PS: Pretending that placebos don't have serious ethical and epistemological problems and dismissively labelling evidence as instead "anecdotes" manages only to underscore just how pernicious this "gold standard" fallacy is.kairosfocus
August 20, 2020
August
08
Aug
20
20
2020
08:28 PM
8
08
28
PM
PST
ET
The EVMS has put out a list of OTC supplements that will do the job of preventing the pandemic we are currently mired in.
Are these the same OTC supplements that the EVSM state have not been demonstrated to have any prophylactic benefits but that there is no harm in taking them?Mac McTavish
August 20, 2020
August
08
Aug
20
20
2020
04:16 PM
4
04
16
PM
PST
A Chinese doctor who was at the epicentre of the COVID-19 outbreak in Wuhan has warned against developing treatments based on anecdotes rather than evidence, adding that there is “no magic bullet” for the disease. Professor Cao Bin, vice-director of the National Clinical Research Centre for Respiratory Disease in China, had moved from Beijing to Wuhan to help during the initial surge of COVID-19 cases in China. Speaking at a National University of Singapore (NUS) webinar on Thursday (Aug 20), Prof Cao recalled that during the early days of the pandemic, people were grasping at straws to find a treatment for COVID-19. “We have heard a lot of stories about the successful treatment of this disease, such as a new drug, or even a kind of drink … for the ill patients,” he said. “But unfortunately, there is no magic bullet – not only during the early days, but for now.” He detailed how hydroxychloroquine was initially granted approval by the US Food and Drug Administration (FDA) after US President Donald Trump touted it as way to ward off the coronavirus. Treating some COVID-19 patients is “complicated”, with some developing severe pneumonia, kidney injury and cardiac injury, said Prof Cao. “Even during a pandemic, even during fear or helplessness, we clinicians should trust evidence, and we should not trust anecdotes,” Prof Cao added. “I think smart clinicians should make clinical decisions based on evidence, even in the era of COVID-19.” Prof Cao was one of the first doctors in the world to use antiviral drugs lopinavir and ritonavir – normally given to HIV patients – to treat COVID-19 patients. “You can tell that as doctors, you want to find a magic bullet. To tell you the truth, this is what I thought in the early days of January 2020. “My colleagues and I wanted to get a kind of magic bullet, but after … we have gathered all the evidence … I have to admit that it’s hard to get a kind of magic bullet.” https://www.channelnewsasia.com/news/asia/covid-19-coronavirus-wuhan-china-singapore-treatment-evidence-13038720rhampton7
August 20, 2020
August
08
Aug
20
20
2020
03:02 PM
3
03
02
PM
PST
Why RCTs are important: Doctors form Boston Medical Center (BMC) showed in a recent study that interleukin-6 inhibitors like sarilumab and tocilizumab can reduce mortality in severe COVID-19 cases. We mentioned at the time that the research wasn’t a randomized, double-blind, placebo-controlled study, but rather an observational one. This brings us to Roche’s version of tocilizumab — Actemra — which has been featured in news reports dating as far back as mid-April. The Swiss drugmaker started a Phase 3 study of the rheumatoid arthritis drug back in mid-March, and the conclusions arrived a few weeks ago. As BioSpace explained in late July, Roche’s San Francisco-based partner Genentech announced that the COVACTA study did not meet its “primary endpoint of improved clinical status in hospitalized adult patients with severe COVID-19 associated pneumonia.” Furthermore, “the key secondary endpoints, which included the difference in patient mortality at week four, were not met.” In other words, this version of tocilizumab combined with standard care could not improve the condition of COVID-19 patients or prevent deaths. We can now add another new drug to the list of failures: tocilizumab, a promising drug that we’ve seen mentioned in a variety of studies, but which has proven to be ineffective in its Phase 3 trial. There is a silver lining here, as researchers observed a positive trend in discharge times with patients who received Actemra. Placebo patients needed 28 days to leave the hospital, while those on Roche’s tocilizumab left after 20 days. The study was still a failure though, since the primary endpoint was not met. https://bgr.com/2020/08/20/coronavirus-cure-tocilizumab-actemra-phase-3-results/rhampton7
August 20, 2020
August
08
Aug
20
20
2020
02:52 PM
2
02
52
PM
PST
Continued... Here's what we can say about HCQ: There is no conflict of interest at play. Hospitals don't make money taking care of COVID-19 patients. In fact, they lose money, even with government bailouts. Health care professionals are taking pay cuts or getting laid off. If cheap HCQ could get us back to business as usual—making money doing elective surgical procedures—and writing these prescriptions would help us secure our jobs and our pay, hospitals would be giving it out for free given the amazing return on investment. Furthermore, the easiest and quickest thing to do for providers would be to just write the prescription, which some are. But it's not the right thing to do. Let's say you were to go into a fatal heart rhythm, a known side effect of HCQ, and die. How could we defend our decision to a jury, let alone to your bereaved family? Referencing a video posted on Twitter, even a viral one, would be woefully insufficient. To prescribe something that can harm without helping violates our most fundamental oath. We were hopeful at first that HCQ would work for COVID-19. It showed promise in the lab and in small human studies. But, ultimately, our wishful thinking did not pan out. https://www.newsweek.com/coming-clean-about-hydroxychloroquine-opinion-1526225rhampton7
August 20, 2020
August
08
Aug
20
20
2020
02:47 PM
2
02
47
PM
PST
at first we said HCQ might work. In fact, some providers were guilty of self-prescribing and hoarding it. Now we say it doesn't work for COVID-19 and could actually do harm. But not everyone believes us, including the president and several members of his administration, as well as many of our own patients. We in health care are quick to dismiss our mixed messages by saying, "Oh, that's just how science works." And, yes, science is a messy process. But that's not the only reason we get things wrong. The truth is, we're human and influenced by more than just science. Sometimes, we engage in wishful thinking. We assume that because something should work, it will work. For example, if you have chronic chest pain due to a blocked coronary artery, doesn't it just make sense to prop it open with a stent? And if you come in with knee pain, and we see torn cartilage on MRI, surely an operation to fix it will give you relief? Well, it turns out that in many cases, those stents are no better than low-cost medications and that knee surgery is no better than physical therapy. We have had to learn (and re-learn) the hard lesson that intuition is not always a reliable guide to illness and health. Sometimes, we succumb to conflicts of interest, even if we are not always conscious of them. When there is more money to be made in stenting an artery or operating on a knee, it makes it harder for us to simply prescribe a medication or send a patient to physical therapy. Sometimes, we just want to make our patients happy. In fact, our livelihoods can depend on it. Providing evidence based care does not always correlate with patient satisfaction. Sometimes, we're simply pressed for time. It might take 30 seconds for a clinician to say yes to a patient's request for an antibiotic to treat the common cold, but 30 minutes to have a conversation explaining why it won't help. https://www.newsweek.com/coming-clean-about-hydroxychloroquine-opinion-1526225rhampton7
August 20, 2020
August
08
Aug
20
20
2020
02:45 PM
2
02
45
PM
PST
1 … 9 10 11 12 13